
Pleural Effusion

By the end of this post you will be able to:
- Recognize the bedside and imaging findings of a pleural effusion and select the initial investigations.
- Apply Light’s criteria — and the albumin gradient when they mislead — to classify an effusion as a transudate or an exudate.
- Identify a complicated parapneumonic effusion or empyema and initiate drainage.
TL;DR
What you need to know before seeing your first patient on your IM rotation with this condition
Estimated read time: 3 minutes

- What it is: Fluid in the space between the lung and the chest wall. The first fork is why: a transudate means the pressures are wrong — heart failure, cirrhosis, nephrotic syndrome. An exudate means the pleura itself is involved — infection, malignancy, inflammation.
- How it presents: Progressive breathlessness, sometimes with pleuritic pain or a dry cough. The JAMA Rational Clinical Examination found the two most helpful findings are dullness to percussion and reduced tactile fremitus over the fluid; absent breath sounds supports them. A normal chest examination does not rule out a small effusion.
- Initial tests to order: Chest radiograph, PA and lateral — the lateral is the more sensitive. Then bedside lung ultrasound, which finds smaller volumes and shows loculation. And the step most often forgotten: draw serum protein, LDH and albumin the same day you tap — Light’s criteria are ratios, and without the serum values the fluid cannot be interpreted.
- If unstable: A large effusion causing respiratory compromise needs therapeutic drainage, not a diuretic — and stop at about 1.5 litres in one sitting.
- If stable — the effusion of unclear cause: Do a diagnostic thoracentesis. Send protein, LDH, pH, glucose, cell count and differential, Gram stain and culture, and cytology. Three things decide whether the results are usable: pH in a blood-gas syringe, on ice; culture into blood culture bottles; and at least 50 mL for cytology.
Listen

Read Around the Case
Based on the British Thoracic Society Guideline for Pleural Disease (2023) and the ATS/STS/STR guideline on Management of Malignant Pleural Effusions (2018). There is no Canadian Thoracic Society guideline on pleural disease.
Estimated read time: 16 minutes
1. Thoracentesis — Confirming the Effusion, and Doing the Procedure
Estimated read time: 4 minutes
The Effusion Sequence
Chest radiograph, PA and lateral
Confirm, estimate volume, look for septations, mark the site
Bilateral, clear heart failure, no fever → treat and reassess.
Unilateral, febrile, pleuritic or unexplained → tap it
Fluid protein, LDH, pH, glucose, cell count, Gram stain and culture, cytology
+ same-day serum protein, LDH and albumin
- Heart failure (the most common cause)
- Hepatic hydrothorax
- Nephrotic syndrome
- Severe hypoalbuminaemia
→ Treat the underlying cause
- Parapneumonic effusion and empyema
- Malignancy
- Pulmonary embolism
- Tuberculosis
- Connective tissue disease
- Pancreatitis, chylothorax
→ Establish the underlying cause
These lists are not exhaustive — they are the causes you will meet most often on a medical ward.
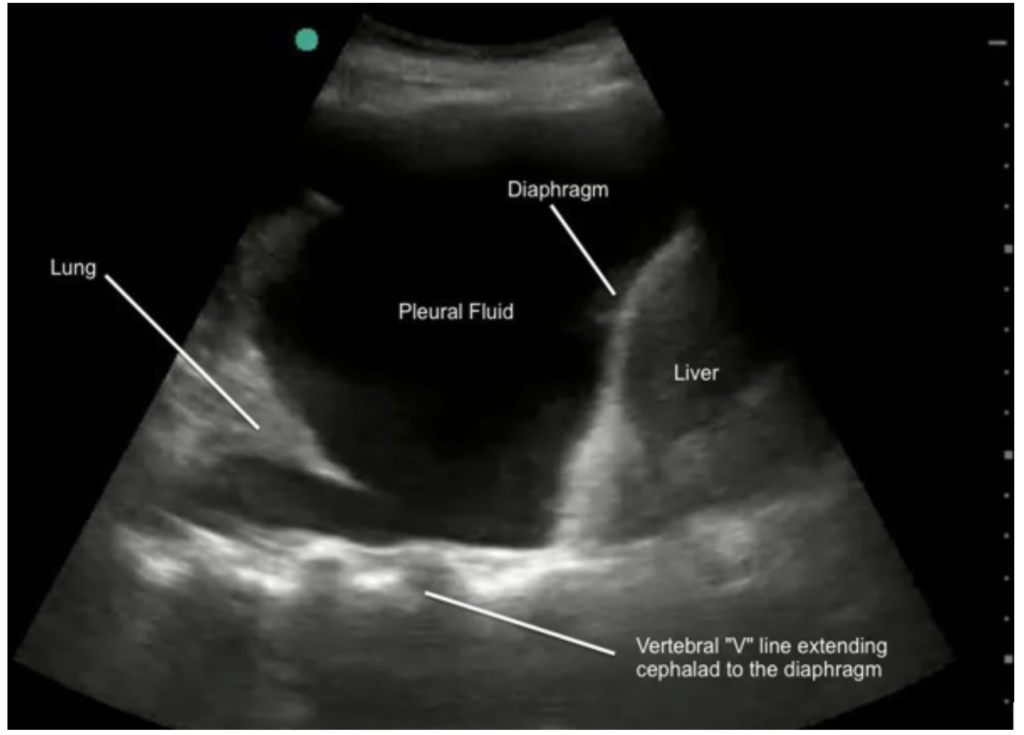
Confirming it is there. It takes roughly 200 mL to blunt a costophrenic angle on a PA film but only about 50 mL on a lateral, which is why a normal-looking PA does not exclude an effusion. Ultrasound beats both: smaller volumes, fluid told apart from consolidation, and septations no radiograph shows. Two findings to know by name are anechoic fluid with atelectatic lung floating in it and the spine sign — the thoracic spine stays visible above the diaphragm, where aerated lung would scatter the beam.
Performing a Thoracentesis
Set up
The tap
Afterwards. Although this varies with local practice and physician comfort, it is worth noting that Petersen & Zimmerman (Chest 2000) found no routine chest radiograph is needed after an uncomplicated tap in a patient who feels well — and that aspirating air predicts pneumothorax, while pain, hypotension and a dry tap do not. Film the patient who had air aspirated or who becomes breathless, not the one who found it sore.
Coagulation — more permissive than most people assume
The Society of Interventional Radiology guidelines (endorsed by the Canadian Association for Interventional Radiology) call thoracentesis low bleeding risk: no prophylactic platelets at ≥ 20 × 10⁹/L (20,000/µL), and no correction of a therapeutic warfarin INR. The 2025 CHEST guideline agrees, and Hibbert et al. found no excess bleeding. Transfusing to a number usually treats the chart, not the patient, and an urgently needed drain should not wait on an INR — local policy may still ask, so know yours.
2. Light’s Criteria, and the Fluid That Lies
Estimated read time: 4 minutes
An effusion is an exudate if any one of Light’s criteria is met:
- pleural fluid protein ÷ serum protein > 0.5
- pleural fluid LDH ÷ serum LDH > 0.6
- pleural fluid LDH > two-thirds of the upper limit of normal serum LDH
Meeting none makes it a transudate. The criteria deliberately over-call exudates — the right trade-off when the alternative is missing an empyema or a malignancy.
The fluid that lies: the pseudoexudate
A patient diuresed for several days will produce fluid that meets Light’s criteria even though the effusion is a transudate. In Romero-Candeira et al., serial taps during diuresis showed pleural protein rising from 23 to 33 g/L and LDH from 177 to 288 U/L in five days — earning the patient a CT, a repeat tap and a consult for an effusion that was always cardiac.
When the numbers say exudate but the patient says heart failure, calculate the gradients:
- serum albumin − pleural fluid albumin > 12 g/L → transudate
- serum protein − pleural fluid protein > 31 g/L → transudate
The same study showed why: diuresis moved the gradients far less than the ratios. Trust the gradient here, and only here.
When the exudate is neither pneumonia nor cancer, the pattern of results narrows it.
Trial Files

3. Parapneumonic Effusion and Empyema — When Antibiotics Stop Being Enough
Estimated read time: 4 minutes
Around 40% of patients admitted with pneumonia develop an effusion. The question is always whether this one needs a drain — and the fluid tells you. The pH is the single most useful number, so send it in a blood-gas syringe on ice: a plain tube or a sample left sitting reads falsely high, and a falsely high pH is the one result that will talk you out of a drain the patient needs.
When to sample, and when to worry. Sample any effusion more than 10 mm deep in a febrile patient with pneumonia. And if fever persists after 48 to 72 hours of appropriate antibiotics, image the chest for an undrained space before broadening antibiotic cover.
Drainage. A small-bore (10–14F) chest tube is first-line, and in most Canadian hospitals it is placed image-guided by interventional radiology, sometimes by respirology. A surgical chest tube is not the first-line device, and asking for one is a common referral error.
Where drainage is incomplete because the space is septated, intrapleural tPA 10 mg plus DNase 5 mg twice daily for three days improves drainage and reduces the need for surgery (MIST2). The detail worth carrying: the combination works and neither drug alone does — tPA breaks the septations, DNase thins the fluid, and either alone was no better than placebo. The earlier MIST1 had already shown intrapleural streptokinase does not work.
Antibiotics should cover anaerobes, for two to six weeks; the pneumonia post covers the choice — this section is about the space, not the drug.
Who to call, and when. Interventional radiology places the image-guided drain or a tunnelled catheter. Respirology for a diagnostic problem, a trapped lung, or thoracoscopy. Thoracic surgery when the patient is not improving despite a functioning drain and intrapleural therapy — a VATS washout or decortication is sometimes the only thing that clears an organized empyema. Fluid that stops draining before the effusion is gone means a blocked catheter or a trapped lung, and a tube that stops swinging with respiration is blocked, kinked or out of the pleural space — all need imaging, not waiting.
4. Malignant Pleural Effusion
Estimated read time: 4 minutes
A malignant effusion usually marks the point at which the disease becomes incurable, and the goal shifts to breathlessness that does not come back. Lung and breast cancer and lymphoma cause most of them.

Getting the diagnosis. Cytology on the first tap is positive in roughly 60%; a second adds a little, a third almost nothing. If it stays negative and suspicion remains, thoracoscopy with pleural biopsy is diagnostic in over 90%.
Relieving the breathlessness. Two things decide the option: whether the lung re-expands after drainage, and how long the patient is likely to live.
TIME2 and AMPLE both compared an indwelling catheter against talc pleurodesis: breathlessness improved equally, but the catheter group spent fewer days in hospital, at the cost of more catheter problems such as blockage and cellulitis. The ATS/STS/STR guideline accepts either where the lung re-expands, and the catheter where it is trapped — pleurodesis cannot work if the pleural surfaces never meet.
What an indwelling pleural catheter involves — the palliative route. A day procedure under local anaesthetic, usually by interventional radiology, tunnelled under the skin. The patient or a home-care nurse drains it at home every two to three days: no admission, no repeat needles. In about half the pleural surfaces seal on their own (auto-pleurodesis) and it comes out. Involve palliative care early — breathlessness here responds to more than drainage.
Listen

Related Podcasts
Test Yourself
Click on your answer to reveal the explanation.
A 68-year-old man is admitted with three weeks of progressive breathlessness. His blood pressure is 128/76 mmHg and has been stable, heart rate 88, temperature 36.9°C, oxygen saturation 93% on room air. There is dullness to percussion and absent breath sounds at the right base. A chest radiograph shows a moderate right-sided pleural effusion. He undergoes an ultrasound-guided diagnostic thoracentesis. The pleural fluid protein is 38 g/L and the pleural fluid LDH is 320 U/L. Serum drawn the same morning shows protein 68 g/L and LDH 420 U/L, with a laboratory upper limit of normal for serum LDH of 250 U/L.
How should this fluid be classified, and what is the most appropriate next step?
A 62-year-old woman is on day 3 of ceftriaxone and azithromycin for community-acquired pneumonia. Her blood pressure is 118/72 mmHg and has been stable throughout, but she has continued to spike fevers to 38.6°C. A repeat chest radiograph shows an enlarging left pleural effusion. Bedside ultrasound demonstrates a moderate effusion with multiple septations. Blood cultures from admission are negative. An ultrasound-guided diagnostic thoracentesis yields turbid fluid with a pH of 7.08, glucose 2.1 mmol/L, LDH 1,450 U/L, and a negative Gram stain.
After reversible causes of ongoing fever have been addressed, what is the most appropriate next step?
Reflect
A 74-year-old woman with heart failure with reduced ejection fraction was admitted three days ago with bilateral pleural effusions. She has been on intravenous furosemide since admission and has lost 4 kg, her jugular venous pressure has fallen and her legs are visibly less swollen — but she is no less breathless than she was on day one, and the right effusion looks unchanged on today’s radiograph. At what point does “it is just her heart failure” stop being a reasonable assumption, and what would you do next?
Please do not include patient identifying details — no names, initials, dates, medical record numbers, or any detail that could identify a specific patient or encounter. Write about your reasoning, not about a real person.
Further Reading
- GuidelineBritish Thoracic Society Guideline for Pleural Disease (Thorax, 2023)
- GuidelineManagement of Malignant Pleural Effusions — ATS/STS/STR Clinical Practice Guideline (2018)
- TrialTIME2 — Indwelling pleural catheter vs talc pleurodesis for malignant effusion (JAMA, 2012)
- TrialMIST2 — Intrapleural tPA and DNase in pleural infection (NEJM, 2011)
Week 2